Healthcare happens when we aren't at our best
Published on September 24, 2026
Summary
Virtual healthcare can make healthcare easier to reach for disabled people. We may not need to arrange accessible transportation or travel to a clinic. But virtual healthcare can have accessibility barriers too. Disabled people often use healthcare when we're sick, tired, in pain, or worried. Barriers can be harder to deal with at those times. Healthcare organizations need to make the whole virtual healthcare process accessible. This includes technology from other companies.
In 2020, I watched virtual healthcare go from something that was growing gradually to something that was suddenly necessary.
COVID changed the timeline. Across the healthcare industry, organizations needed ways for patients to see doctors without sitting in waiting rooms or sometimes leaving their homes at all. Things that might have taken years to plan and implement had to happen much faster.
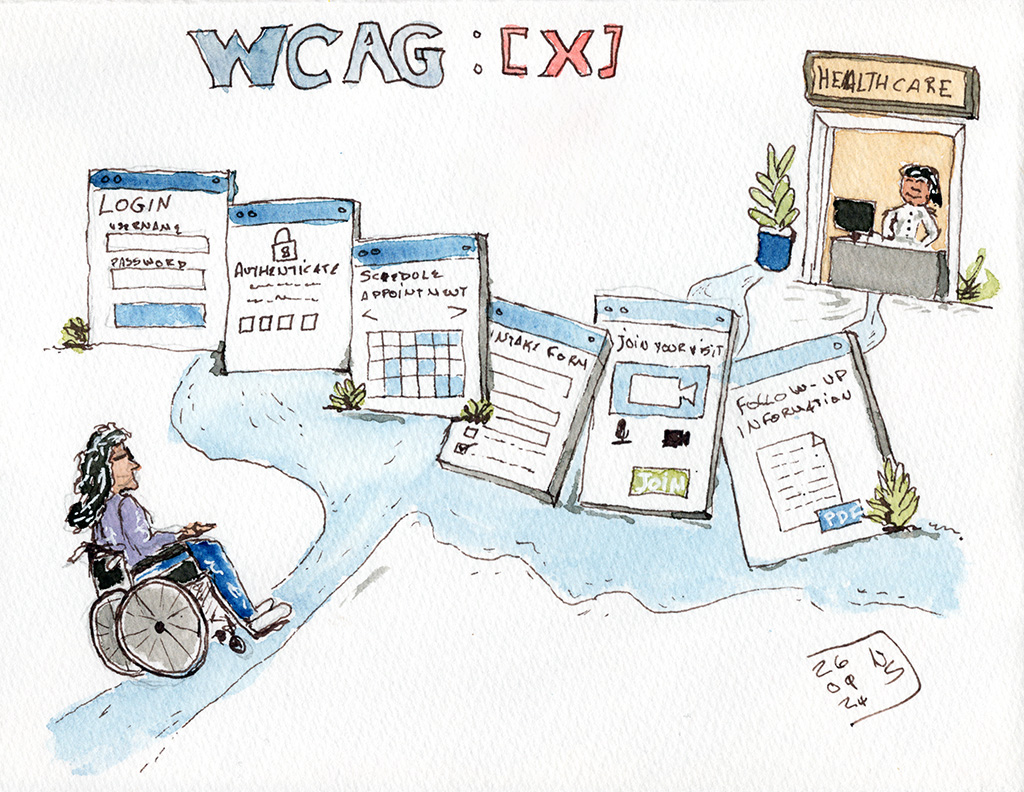
I was working in digital accessibility while that shift was happening. There was a lot of urgency, for good reason. People needed healthcare, clinicians needed ways to reach them, and nobody knew how long the situation would last.
Moving healthcare online quickly didn’t mean that everyone could use it.
That wasn’t a new problem. Disabled people had already been dealing with inaccessible healthcare websites, forms, patient portals, documents, and other digital systems. COVID changed the scale of virtual healthcare and made the consequences of those barriers much harder to ignore.
An inaccessible form is a problem anywhere. When that form stands between you and an appointment with a doctor, the stakes are different.
The same applies to authentication you can’t complete, a scheduling interface you can’t operate, a video platform that doesn’t work properly with your assistive technology, or follow-up information you can’t read. All of these affect whether a disabled person can get healthcare independently.
Disabled people don’t arrive at healthcare with only one barrier
Accessibility is for disabled people. I don’t think we need to make a case for accessible virtual healthcare by first demonstrating that nondisabled people will benefit from it too.
Disabled people need healthcare. We need to book appointments, explain symptoms, understand what clinicians tell us, manage prescriptions, read test results, make decisions, and get follow-up care.
Whatever brought us to the doctor may also make the accessibility barriers we already encounter harder to deal with.
A blind person using a screen reader may also have pneumonia and be exhausted. A Deaf person may be trying to understand unfamiliar information about a new diagnosis. A cognitively disabled person may be trying to follow complicated instructions while frightened about what those instructions mean.
I’ve spent decades thinking about barriers disabled people encounter with technology. Healthcare is different because we often interact with these systems when we have less energy available to work around bad design.
Disabled people become remarkably good at working around barriers. We shouldn’t have to, but we do. We learn which browser works better with a particular website. We find another route to something. We try again. We develop strategies for dealing with technology that wasn’t designed with us in mind. None of this is a particularly good use of our time, but we get a lot of practice.
Working around those barriers becomes a lot harder when you’re sick, exhausted, in pain, or worried about what a doctor is going to tell you.
Virtual healthcare can remove barriers
One thing I don’t want us to lose from the experience of the last several years is just how useful virtual healthcare can be for disabled people.
Getting to a doctor’s appointment isn’t always simple. You may have to arrange accessible transportation. The trip itself may take considerable time and energy. The building may have barriers. The examination room may have barriers. Waiting rooms aren’t necessarily easy places to spend time. For some disabled people, going into a healthcare setting also brings increased exposure to respiratory illness and other infections.
A virtual appointment can remove some of that. Someone can speak with a clinician from home, using their own computer, their own setup, and the assistive technology they use every day. They don’t necessarily have to spend limited energy getting to and from an appointment just to have a conversation that could have happened remotely.
For that to work, the virtual part has to be accessible.
Think about what might be involved in a single appointment. You may have to log into an account, authenticate yourself, find the right service, book an appointment, complete an intake form, answer questions about your health, join a video call, communicate with the clinician, and then retrieve information afterward.
Inside a healthcare organization, those things may belong to completely different systems.
Authentication might be owned by one team. Scheduling by another. The video platform might come from a third-party vendor. Someone else may be responsible for the patient portal. Follow-up instructions might be generated as a document. Organizations are very good at drawing boxes around systems. Patients have the inconvenient habit of experiencing all the boxes in a row.
If they encounter accessibility barriers at 3 or 4 points along the way, it doesn’t particularly matter that each barrier belongs to a different product team or vendor. Their experience of the appointment includes all of it.
Testing individual screens and components matters, but so does understanding the route a disabled person has to travel through the system. An accessible video call doesn’t help much if the patient can’t get through the process required to join it.
We have had time to do better
I have some sympathy for the decisions healthcare organizations made in 2020.
It was an emergency. People were trying to solve difficult problems quickly, often without knowing what the next month would look like. Clinicians who had spent their careers seeing patients face to face suddenly had to work differently. Patients had to learn new systems. Technology had to be deployed quickly.
Accessibility should have been part of that work, but I can understand how some things went wrong in that environment.
More than 6 years later, that explanation doesn’t work nearly as well.
Virtual healthcare is now part of how healthcare is delivered. The industry has had time to learn which approaches work, where barriers exist, and how virtual care can remove some significant barriers for disabled people.
It has also had time to make accessibility part of the way these systems are designed, bought, built, tested, and maintained.
Digital accessibility is often evaluated one piece at a time. Does the website conform? Does the app work with a screen reader? Can someone use the interface with a keyboard? Those are necessary questions, and I’ve spent a large part of my career asking them.
Healthcare organizations also need to look beyond each individual piece. A patient logs in, fills out an intake form, launches a video app, talks to a clinician, and accesses follow-up information for one reason. They’re trying to get healthcare.
That means accessibility testing has to follow the patient journey too.
Test the authentication. Test the scheduling. Test the forms. Test the virtual visit. Test what happens afterward. Include the third-party products along the way, even when another company owns the code and fixing it is considerably less convenient than finding the problem.
COVID showed the healthcare industry how quickly virtual care could change when circumstances demanded it.
The next step is making sure disabled people can actually use the healthcare systems that are now here to stay.